

Categories
Change Password!
Reset Password!



Updated 2025 consensus guidance refines functional dyspepsia management with new mechanistic insights and personalized care recommendations.
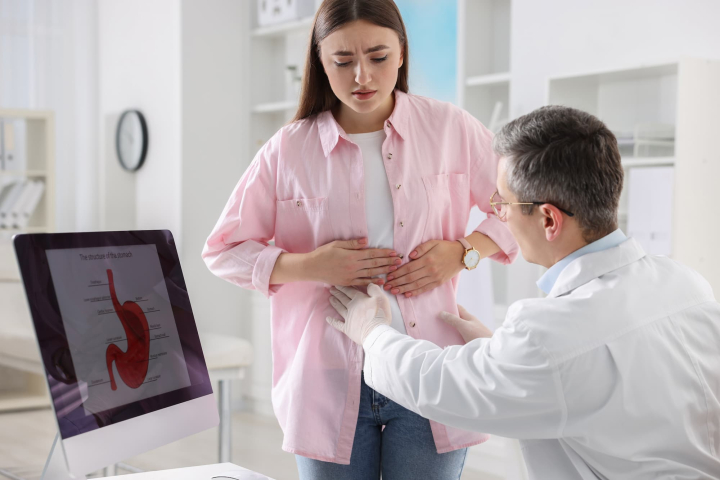
Functional dyspepsia (FD), a common ailment of gut–brain interaction, presents with persistent upper gastrointestinal (GI) symptoms. The condition continues to impose a substantial burden on patients' quality of life (QoL) and healthcare systems, making timely diagnosis and effective symptom management an important clinical priority. More than a decade after the first Asian consensus was published, growing scientific evidence has expanded the understanding of the biological mechanisms underlying FD, creating the need for updated, region-specific recommendations.
To develop the revised guidance, the multidisciplinary task force systematically reviewed the available literature and employed a modified Delphi process to achieve expert consensus. Statements that did not reach the predefined agreement threshold during the initial voting round were refined by incorporating additional evidence and improved clarity before undergoing further discussion and a second round of voting.
This structured process resulted in 32 evidence-based consensus statements addressing the definition, epidemiology, diagnosis, pathophysiology, and management of FD. The updated recommendations reflected the evolving understanding that FD is a multifactorial disorder rather than a condition driven solely by excessive gastric acid or psychological factors. The expert panel highlighted accumulating evidence supporting the roles of impaired gastric accommodation, delayed gastric emptying, visceral hypersensitivity, altered gut–brain communication, and low-grade GI inflammation in symptom development.
These overlapping mechanisms were recognized as key contributors to the variability in clinical presentation and treatment response observed among patients. The consensus reaffirmed that FD should be diagnosed after excluding structural GI disease through appropriate clinical evaluation. The experts emphasized the importance of recognizing alarm features, including unexplained weight loss, GI bleeding, persistent vomiting, dysphagia, and anaemia, as these findings warranted further diagnostic investigation before confirming a diagnosis of FD.
Rather than recommending a one-size-fits-all approach, the report advocated individualized management based on symptom profile and underlying pathophysiological mechanisms. Lifestyle and dietary modifications remained central to treatment, while acid-suppressive therapy, prokinetic agents, neuromodulators, and psychological interventions continued to play important roles in appropriately selected patients.
The panel also assessed emerging therapies but concluded that evidence supporting probiotics and potassium-competitive acid blockers remained limited and heterogeneous. Variability across available studies had prevented definitive conclusions regarding their routine clinical use, underscoring the need for larger, high-quality clinical trials.
Overall, the second Asian consensus report reinforced a mechanism-based, patient-centred approach to FD, providing clinicians with updated guidance while identifying important evidence gaps that should shape future research and therapeutic development.
Journal of Gastroenterology and Hepatology
Second Asian Consensus Report on Functional Dyspepsia (2025): Updated Recommendations
Sanjiv Mahadeva et al.







Comments (0)