

Categories
Change Password!
Reset Password!


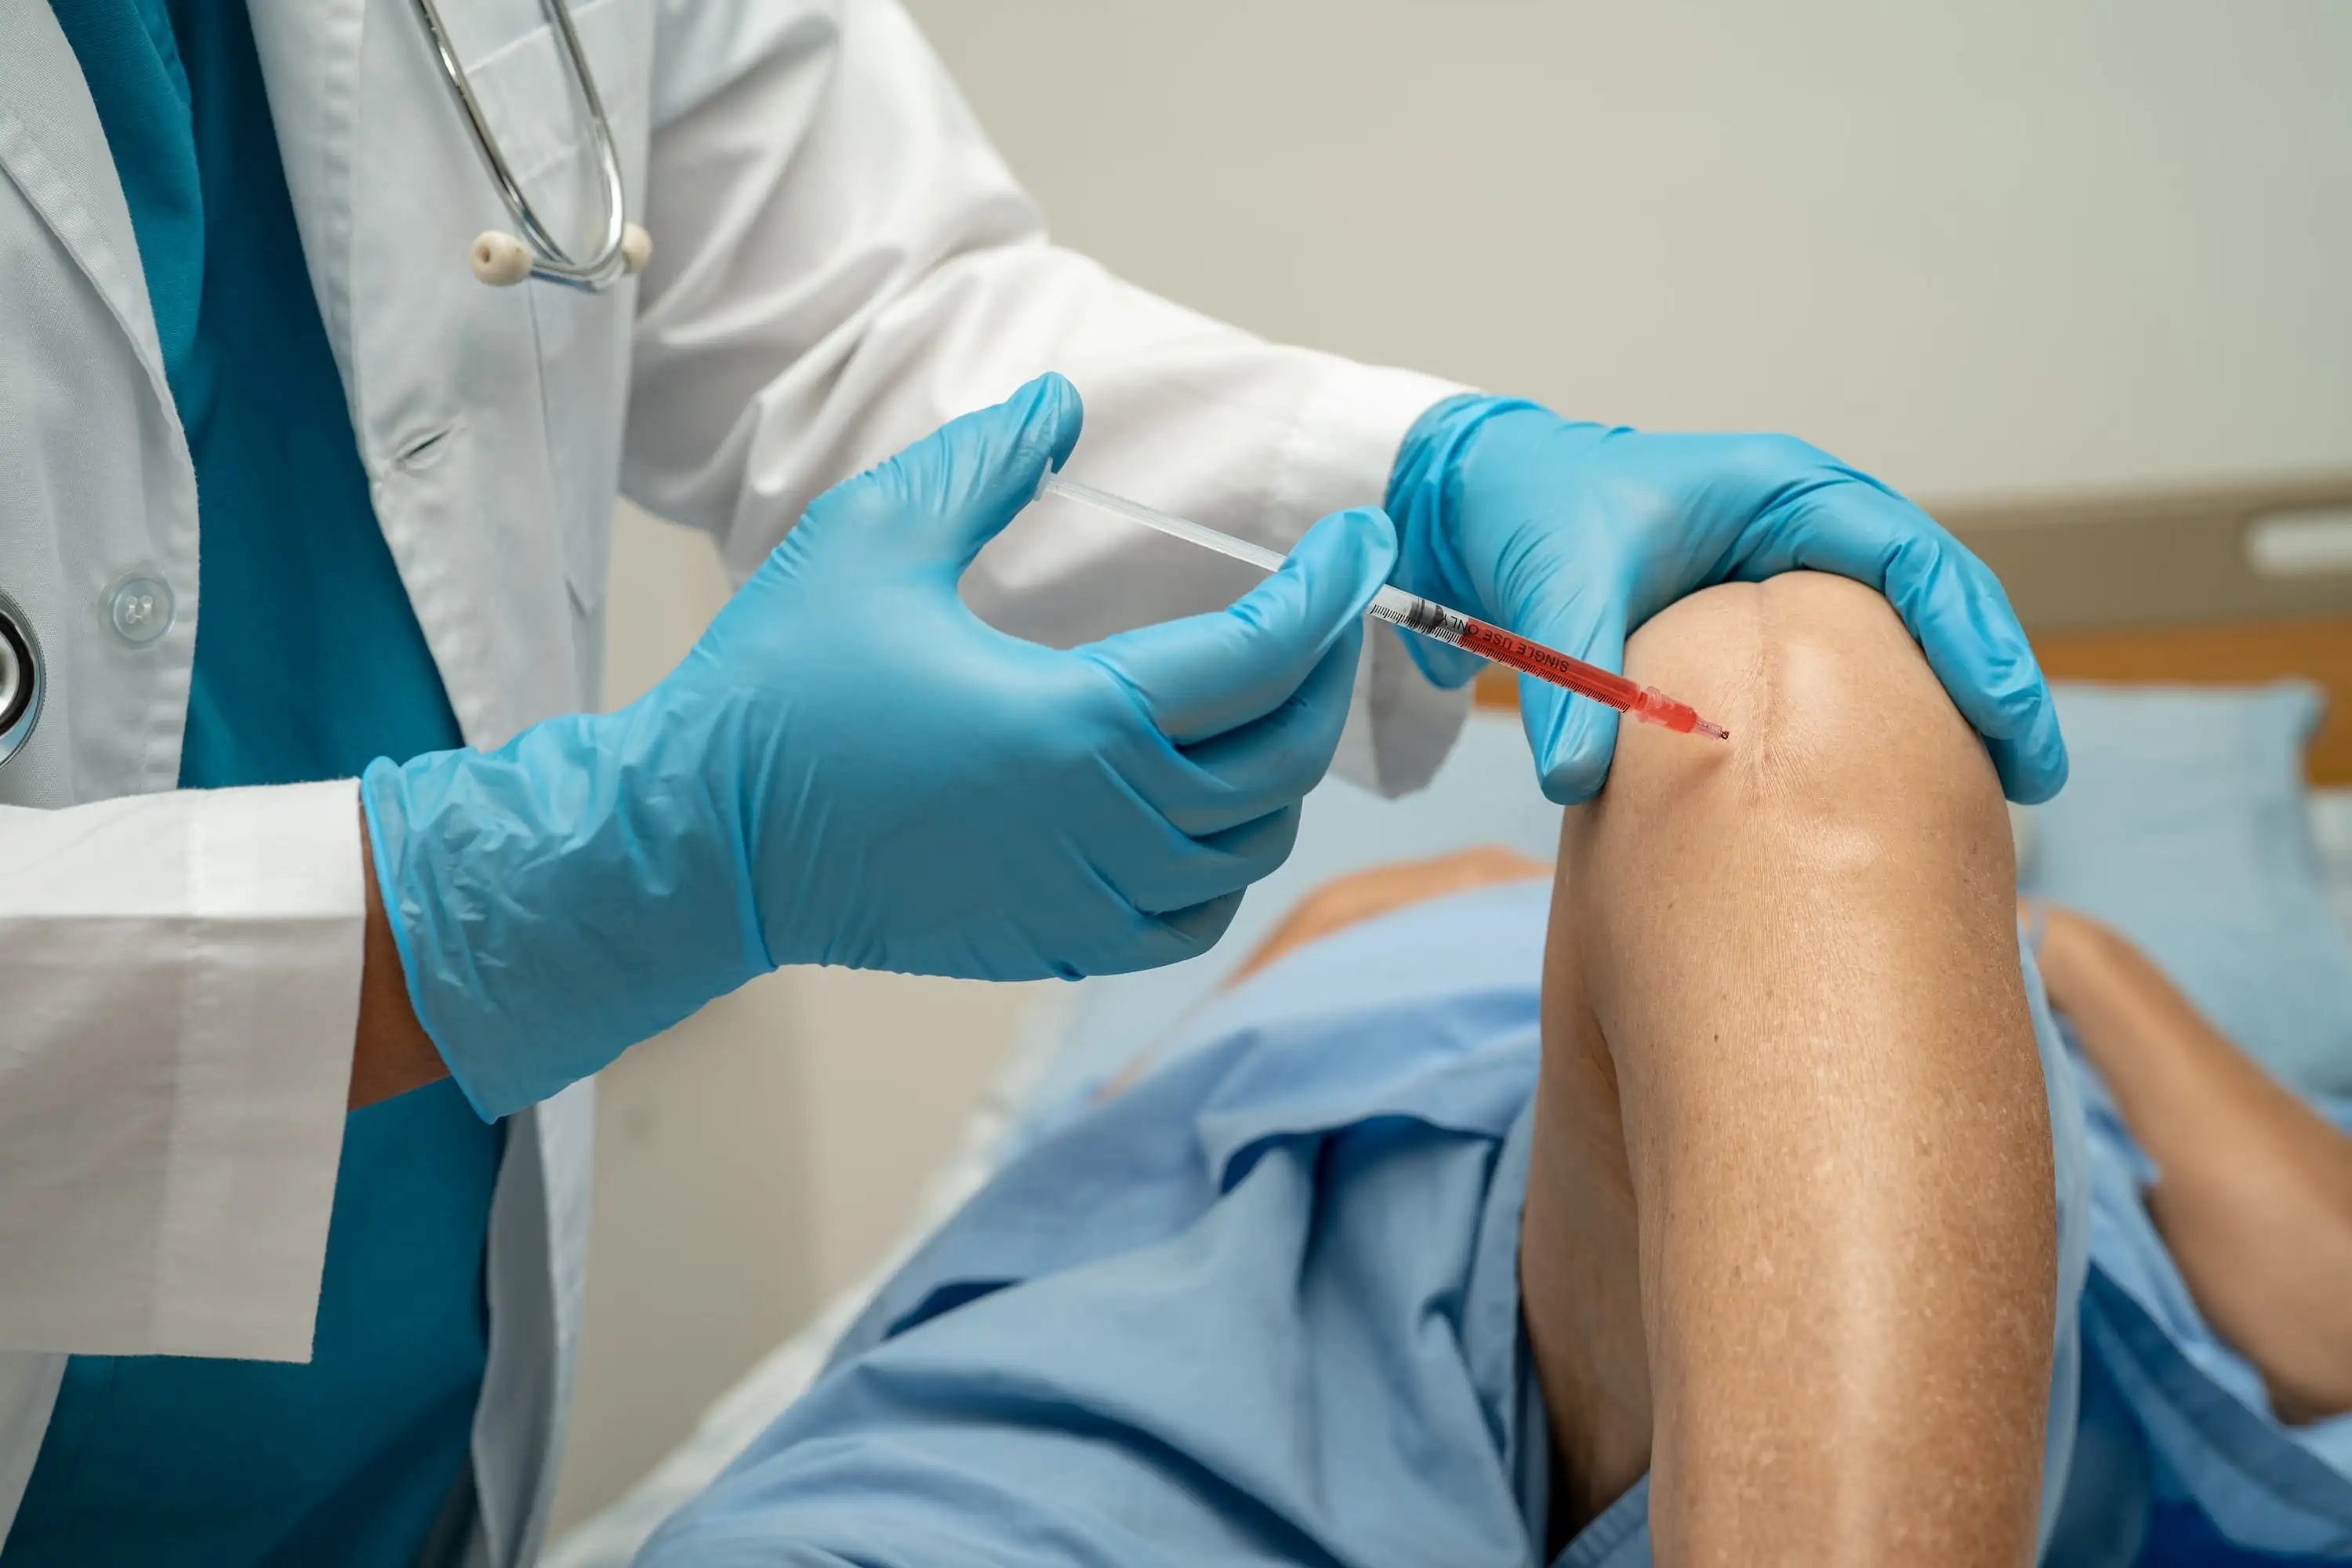
Expert consensus supports intra-articular hyaluronic acid as a patient-centered treatment option for knee osteoarthritis, particularly outside acute flares.
For doctors treating knee osteoarthritis (OA), selecting the right intra-articular therapy depends on disease severity, patient characteristics, expected benefit, and treatment preferences. A novel expert consensus offers practical guidance on the role of intra-articular hyaluronic acid (IAHA) in knee OA, with emphasis on patient selection, efficacy, safety and shared decision-making.
IAHA shows clinical benefit in knee OA
Hyaluronic acid (HA) is a naturally occurring component of synovial fluid, but its concentration and properties decline with progressive knee OA. After nearly five decades of clinical use, evidence from trials, meta-analyses and umbrella reviews continues to support IAHA for symptomatic knee OA.
A 2025 umbrella review of 22 systematic reviews found noticeable benefits with IAHA in 20 reviews. Among the five reviews rated high or moderate quality using Assessing the Methodological Quality of Systematic Reviews-2 (AMSTAR-2), all reported significant beneficial effects. A clinically relevant effect size was approximately −0.37 standard deviations, corresponding to about a 0.9-cm improvement on a 10-cm visual analog scale (VAS).
Which knee OA patients may be suitable?
Response to IAHA may vary as per the patient's clinical profile. Lower treatment response has been linked with:
Nevertheless, these factors do not automatically exclude treatment. IAHA may also be considered in selected patients aged >90 years, those with body mass index ≤40 kg/m², diabetes, or a history of gout when the disease is not acutely active. It may be considered for Kellgren–Lawrence grade 2–3 tibiofemoral OA, symptomatic early OA with normal radiographs, and mild-to-moderate effusions of approximately 1–10 mL. IAHA is not advised during an acute, active OA flare.
What about IAHA safety?
Overall, the consensus considers the safety profile of IAHA favorable. A network meta-analysis covering 74 trials and 13,042 patients found no major systemic safety concerns across 18 IAHA products. However, few meta-analyses reported a potential rise in serious adverse events. One analysis of 14 trials involving 3,667 volunteers reported a risk ratio of 1.41, while an updated analysis reported an odds ratio of 1.86. The consensus emphasizes that these findings must be interpreted cautiously because reported adverse events do not establish causality.
Do combination HA injections offer additional benefit?
IAHA has been combined with mannitol, sorbitol, chondroitin sulphate, tranexamic acid, polynucleotides, corticosteroids and hybrid HA formulations. Evidence for additional benefit varies between formulations. In a meta-analysis of 8 studies, corticosteroid–IAHA combinations produced greater reductions in Western Ontario and McMaster Universities Osteoarthritis Index (WOMAC) pain scores than IAHA alone at 2–4 weeks, 24–26 weeks and 52 weeks, without pivotal safety differences. Therefore, clinicians must assess the evidence for the specific HA formulation, rather than assuming that combination products are universally superior.
Patient preference matters
The consensus places shared decision-making at the center of IAHA treatment. Patients may prefer IAHA because it offers a minimally invasive, non-steroidal option with moderate potency and a favorable safety profile. For clinicians, treatment selection must consider the OA phenotype, disease stage, comorbidities, previous treatments, HA formulation, and patient expectations.
Clinical takeaway
IAHA is a potential non-surgical treatment for selected patients with knee OA, with the greatest emphasis on individualized patient selection and avoiding intervention during acute OA flares.
Aging Clinical and Experimental Research
Expert consensus on hyaluronic acid injections for knee osteoarthritis: a patient-centered approach
Nicholas Fuggle et al.










Comments (0)