

Categories
Change Password!
Reset Password!


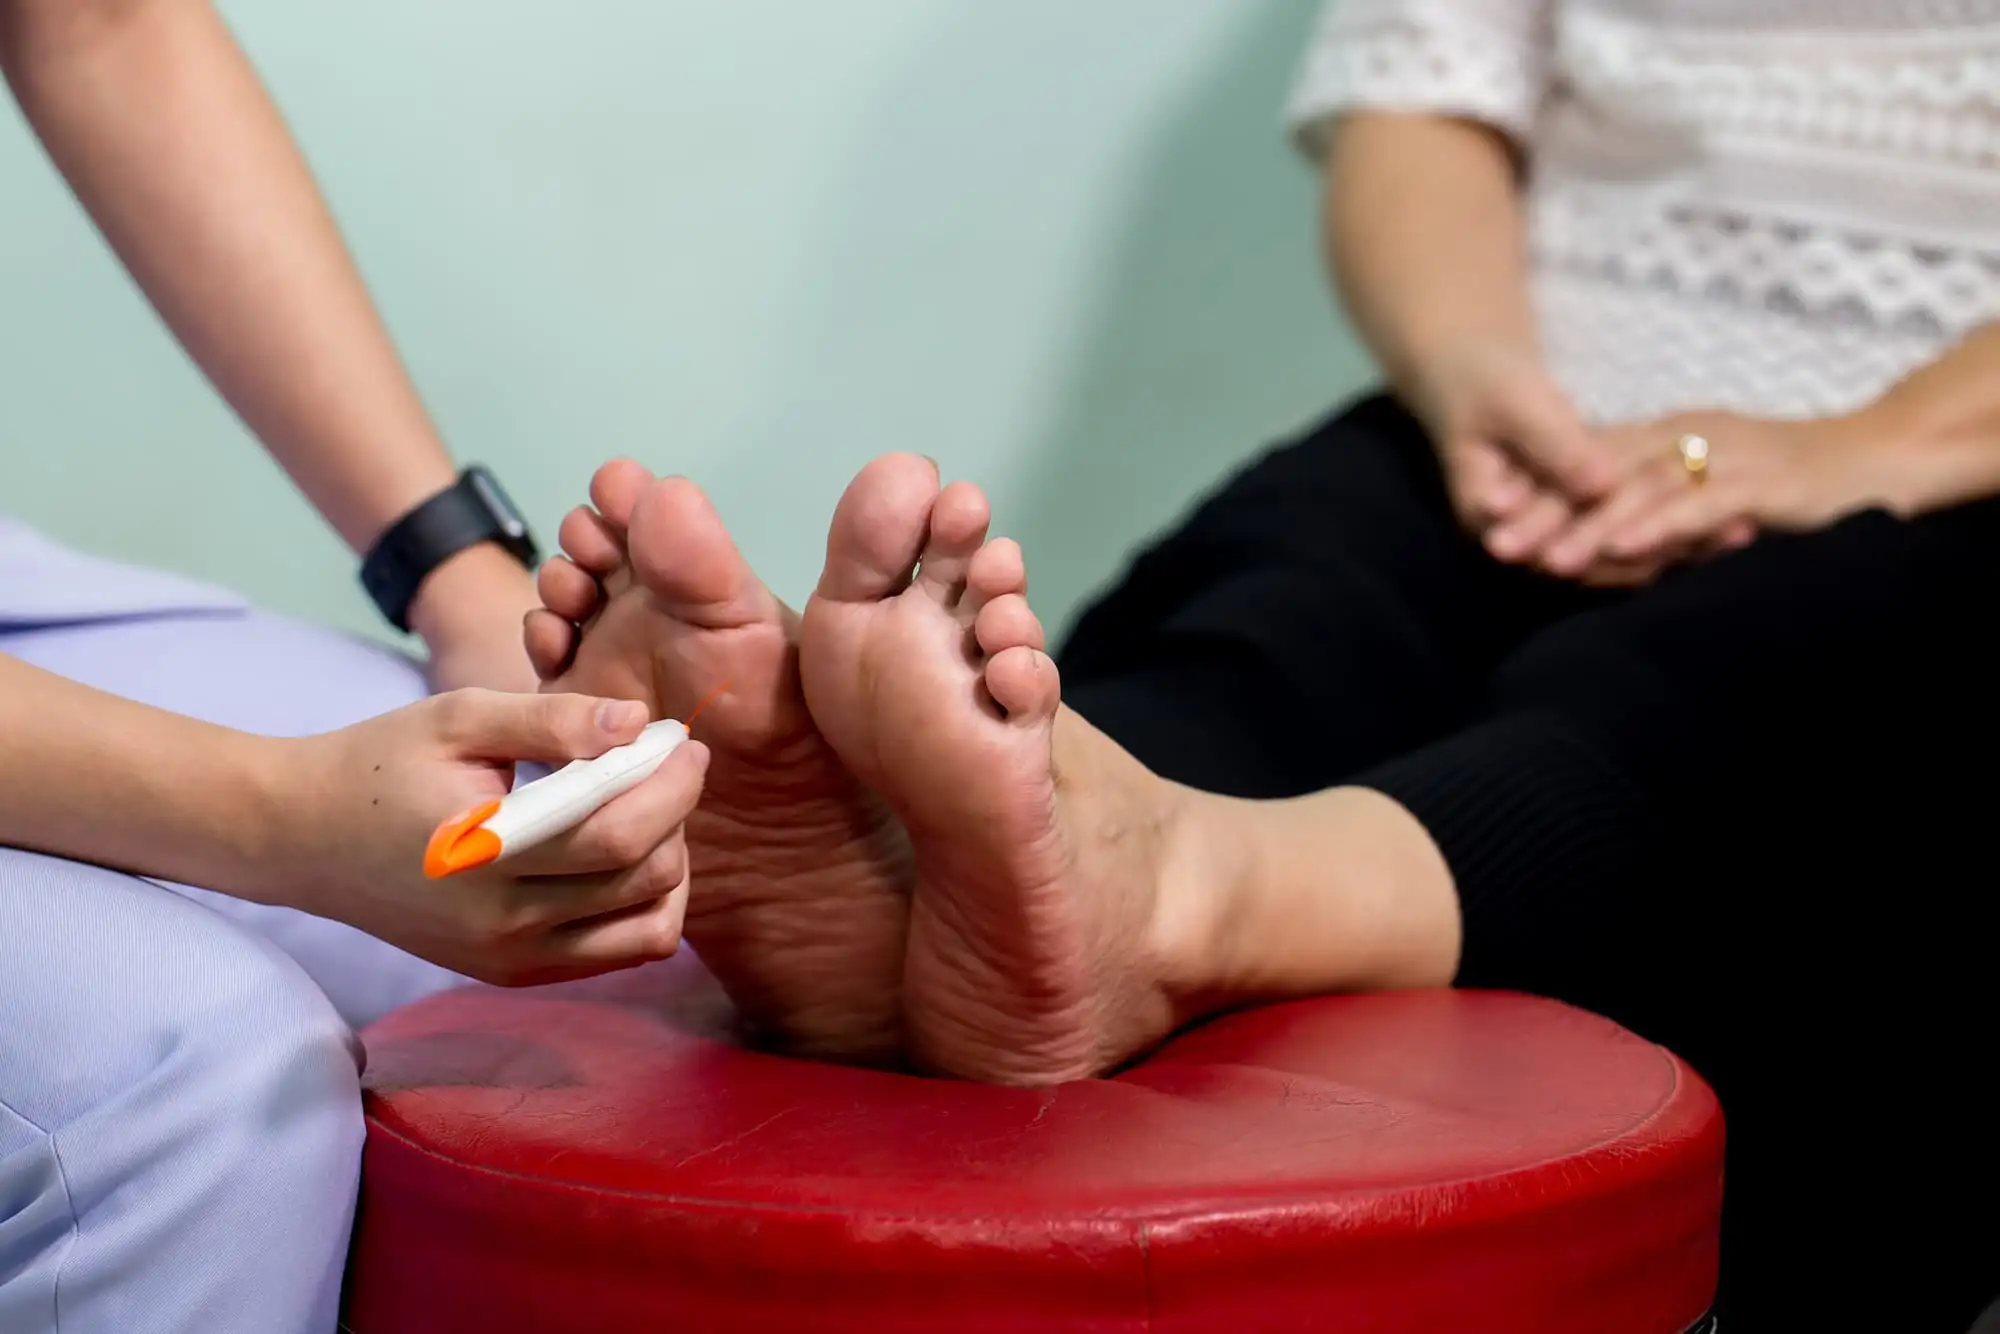
Vitamin B1 and B12 deficiencies are strongly linked to neuropathies while excess vitamin B6—not deficiency—has a clearer association with neurotoxicity.
Peripheral neuropathy can be a manifestation of nutritional deficiency—but the connection differs across the B-vitamin family. A recent review, led by Mauricio Alvarez et al., synthesizes historical and contemporary evidence on vitamins B1, B6, B12, and B9 (folate) and their neurological effects.
B1 deficiency: Think beriberi and Wernicke encephalopathy
Thiamine (vitamin B1) is crucial for neuronal energy metabolism and neurotransmission. Prolonged deficiency can impact both the central and peripheral nervous systems, producing dry beriberi—a symmetric polyneuropathy marked by paresthesia, muscle weakness, and altered deep-tendon reflexes.
Severe deficiency can trigger WE, an acute neurological emergency. Its classic triad comprises encephalopathy, oculomotor dysfunction, and gait ataxia, but all three occur in only about one-third of patients; ataxia may be the earliest manifestation. Autopsy studies report WE in 12.5% of people with chronic alcohol use. Beyond alcohol use, clinicians must consider thiamine deficiency in those with malnutrition, chronic disease, bariatric surgery, pregnancy, advanced age, or chronic diuretic use.
B6: Deficiency link remains uncertain—but excess matters
Vitamin B6 (pyridoxine) supports neurotransmitter synthesis, amino-acid metabolism, homocysteine metabolism and myelin formation. Although deficiency can produce neurological manifestations, including paresthesia, seizures and peripheral neuropathy, evidence for a direct causal relationship between B6 deficiency and peripheral neuropathy remains inconclusive.
A key concern is the opposite: excess B6 exposure is associated with axonal sensory neuropathy, suggesting a potential neurotoxic effect. The review therefore underscores the requisition to consider excessive supplementation when examining unexplained neuropathy.
B12 deficiency: an important reversible cause of neuropathy
Vitamin B12 (cobalamin) is critical for DNA synthesis, fatty-acid metabolism and myelin maintenance. Deficiency can cause peripheral neuropathy, cognitive and psychiatric manifestations, and megaloblastic anemia. Neurological disease may occur without anemia. Neurophysiological abnormalities most commonly involve axonal neuropathy (57–76%), followed by demyelinating neuropathy (5–24%), while nerve-conduction abnormalities are noted in nearly 50–55% of patients with neuropathy symptoms.
For those with borderline serum B12 levels of 200–300 pg/mL, methylmalonic acid (MMA) and homocysteine can yield additional diagnostic information. MMA is considered the more sensitive and specific marker, although availability and cost can restrict its use. Importantly, neurological recovery can be incomplete. Improvement generally occurs over 6–12 months after therapy; one study reported complete neurological recovery in 47% of patients, while 6% developed moderate-to-severe long-term neurological disability. Earlier treatment is linked with better neurological recovery.
Folate deficiency: another potential contributor
Vitamin B9 (folate) is fundamental for DNA synthesis, cell division, and nervous-system development. Folate deficiency can trigger a predominantly sensory peripheral neuropathy, typically with slower progression than thiamine-deficiency neuropathy. The WHO-based criteria are as follows:
A serum folate concentration >25.5 nmol/L (11 ng/mL) is considered optimal for minimizing neural-tube-defect risk.
Clinical message
For those presenting with unexplained peripheral neuropathy, nutritional assessment remains clinically relevant. The review supports a differentiated approach: B1 and B12 deficiencies have well-established neurological consequences; folate deficiency may contribute to predominantly sensory neuropathy; and B6 requires particular caution because excess exposure may itself induce neurotoxicity.
Risk can escalate with alcohol use, malnutrition, bariatric surgery, gastrointestinal malabsorption, restrictive diets, and certain medications. In particular, B12 deficiency must remain on the differential diagnosis of neuropathy even when macrocytic anemia is absent.
Current Nutrition Reports
B Vitamin Deficiencies and Associated Neuropathies
Mauricio Alvarez et al.








Comments (0)