

Categories
Change Password!
Reset Password!



Helicobacter pylori (H. pylori) infection remains a widespread global health challenge, with an estimated 4.4 billion people affected, representing approximately 56% of the world’s population.
β-cyclodextrin–propolis complex enhances the therapeutic potential of standard treatment for H. pylori infection, with improved recovery and symptom relief. It demonstrates favorable physicochemical properties and good tolerability, supporting its potential as an adjunctive therapy.
Helicobacter pylori (H. pylori) infection remains a widespread global health challenge, with an estimated 4.4 billion people affected, representing approximately 56% of the world’s population. The burden of infection is especially high across Africa, South America, and parts of Asia. Conventional eradication regimens generally combine proton pump inhibitors with multiple antibiotics. However, increasing antimicrobial resistance, inadequate treatment adherence, and adverse drug reactions have contributed to reduced eradication success worldwide.
Because of their antimicrobial and gastroprotective effects, natural compounds are being explored as complementary options alongside conventional therapies. Propolis is a resinous material gathered by honeybees from plants and exhibits antibacterial, antiviral, antifungal, anti-inflammatory, antioxidant, and wound-healing activities. However, its therapeutic application is restricted by limited water solubility, instability in aqueous conditions, and poor oral bioavailability.
β-cyclodextrin (β-CD) consists of a hydrophilic outer surface surrounding a hydrophobic internal cavity, allowing it to function as a carrier for poorly water-soluble compounds such as propolis. Incorporating propolis into β-CD produces an inclusion complex that can improve its stability, solubility, and gastrointestinal (GI) absorption while protecting its active constituents from degradation.
Objective
This double-blind, randomized clinical trial assessed the efficacy and safety of a β-CD–propolis complex used as an adjunct to a modified quadruple therapy regimen, compared with placebo, in patients with biopsy-confirmed H. pylori infection.
(a) Study design
A placebo-controlled clinical trial was conducted at Hamadan University of Medical Sciences, Iran. Subjects were allocated via block randomization (25 blocks of four subjects) generated from a simple random number table. Participants, healthcare providers, and data collectors were all kept blinded to group assignment.
(b) Sample size calculation
It was calculated based on prior data from Imani et al., which reported a 26.5% urea breath test (UBT) positivity rate in a cinnamon extract group versus 46.9% in a control group. The investigators anticipated at least a 5% greater potency than cinnamon extract and assumed a 25% between-group difference. This yielded a target of at least 50 participants per group to achieve 80% statistical power at a 5% significance level.
(c) Inclusion criteria
(d) Exclusion criteria
(e) Intervention
Although 100 eligible subjects were randomized, only 28 intervention and 12 control subjects completed the 2-month treatment/follow-up and were included in the reported final analysis.
Both groups were treated with a 2-week course of standard quadruple therapy: bismuth subcitrate 240 mg, amoxicillin 1 g, and metronidazole 500 mg (each twice everyday) plus omeprazole 20 mg once everyday, followed by omeprazole alone for an additional month.
(f) Propolis sourcing and complex preparation
Iranian propolis collected in Aug–Sep 2023 from Taleghan, northern Iran, was extracted with 70% ethanol for 72 hours. Equal weights of propolis and food-grade β-CD were physically mixed and ground for approximately 40 minutes at 20°C and 35% humidity.
(g) Complex characterization
Field-emission scanning electron microscopy (FESEM), dynamic light scattering (DLS), and fourier-transform infrared spectroscopy (FTIR) were used to assess morphology, particle size, and molecular interactions.
(h) Release testing
Propolis release was assessed in phosphate-buffered saline (PBS; pH 7.4) at 37°C, with measurements extending to 48 hours. Dissolution was also assessed in PBS (pH 7.4) and acetate buffer (pH 4.5–5.5).
(i) Outcome measures
(j) Statistical analysis
Datasets were analyzed in SPSS V17 via descriptive statistics, chi-square tests, Fisher's exact test, and t-tests for normally distributed data. The Mann–Whitney U test was applied to nonparametric data. Significance was set at p < 0.05. Fisher's exact test was specifically chosen for the primary efficacy comparison because of the limited final sample size in each arm.
(a) Physicochemical findings
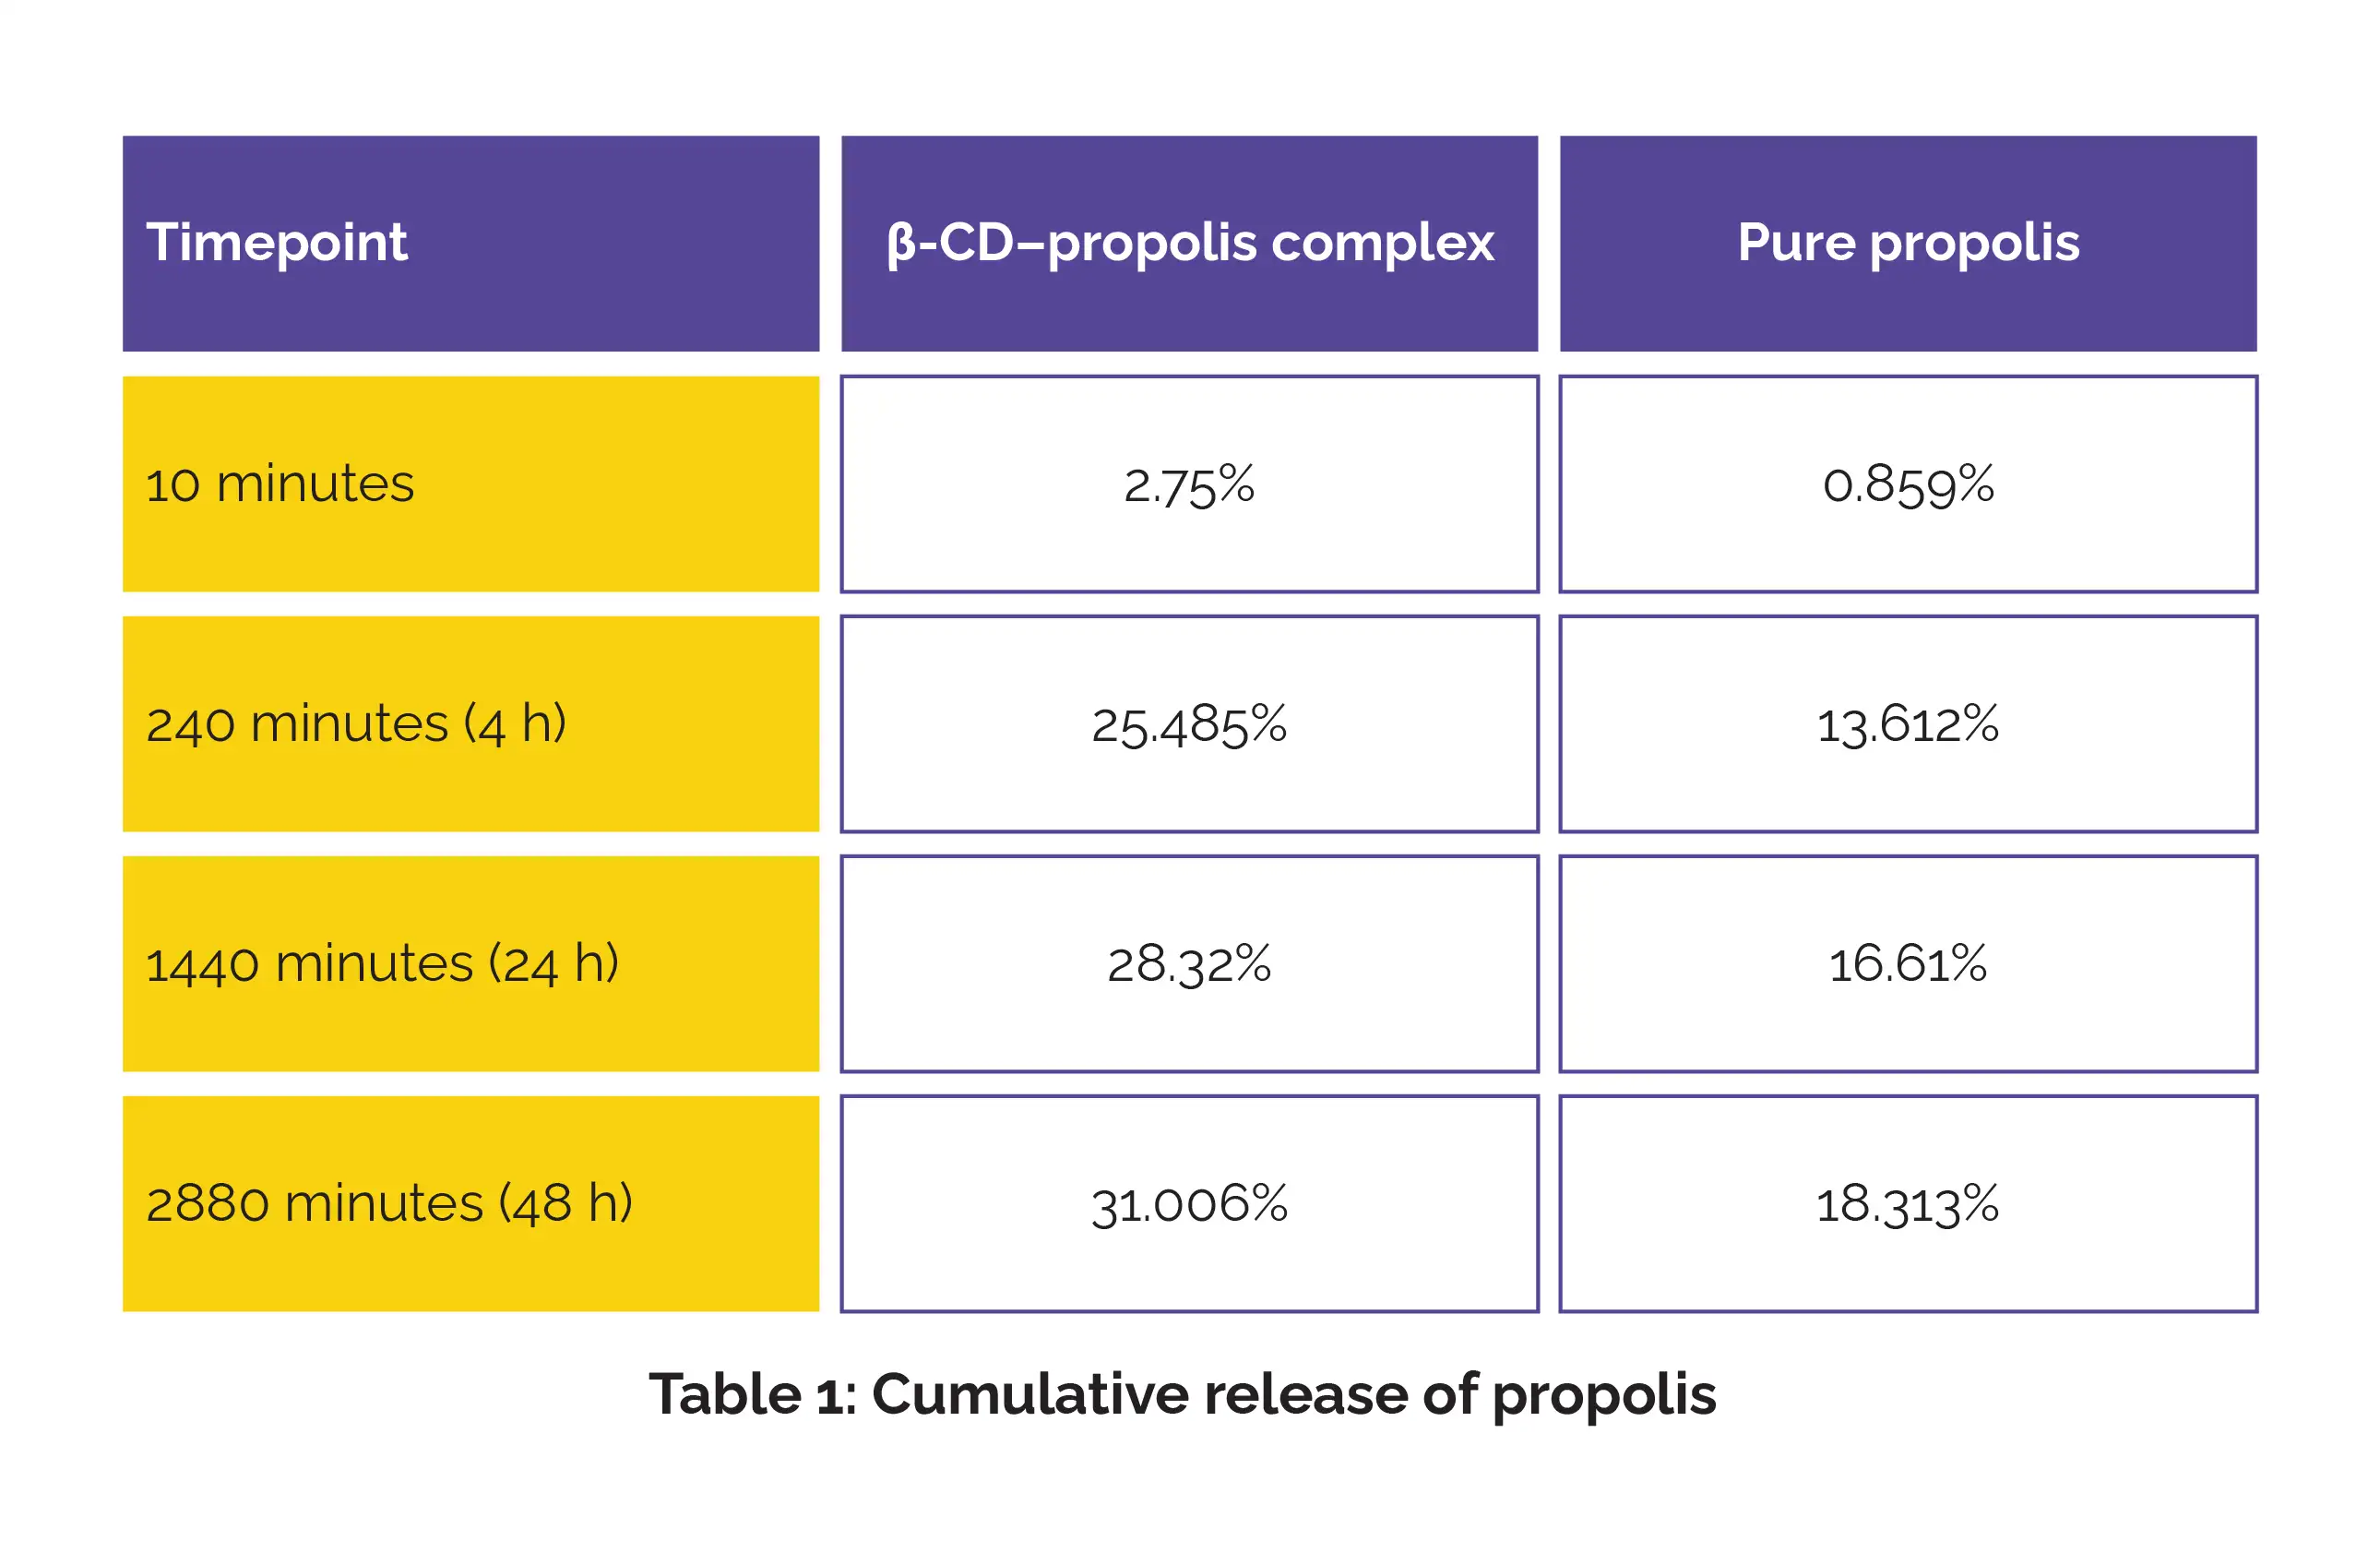
In the dissolution test, release in neutral PBS (pH 7.4) reached 8.27% at 10 minutes and 60.74% at 240 minutes. In acidic acetate buffer (pH 4.5–5.5), release was markedly slower, at 0.4% at 10 minutes and 38.87% by 240 minutes, suggesting pH-dependent release with greater stability under neutral, intestinal-like conditions.
(b) Clinical efficacy
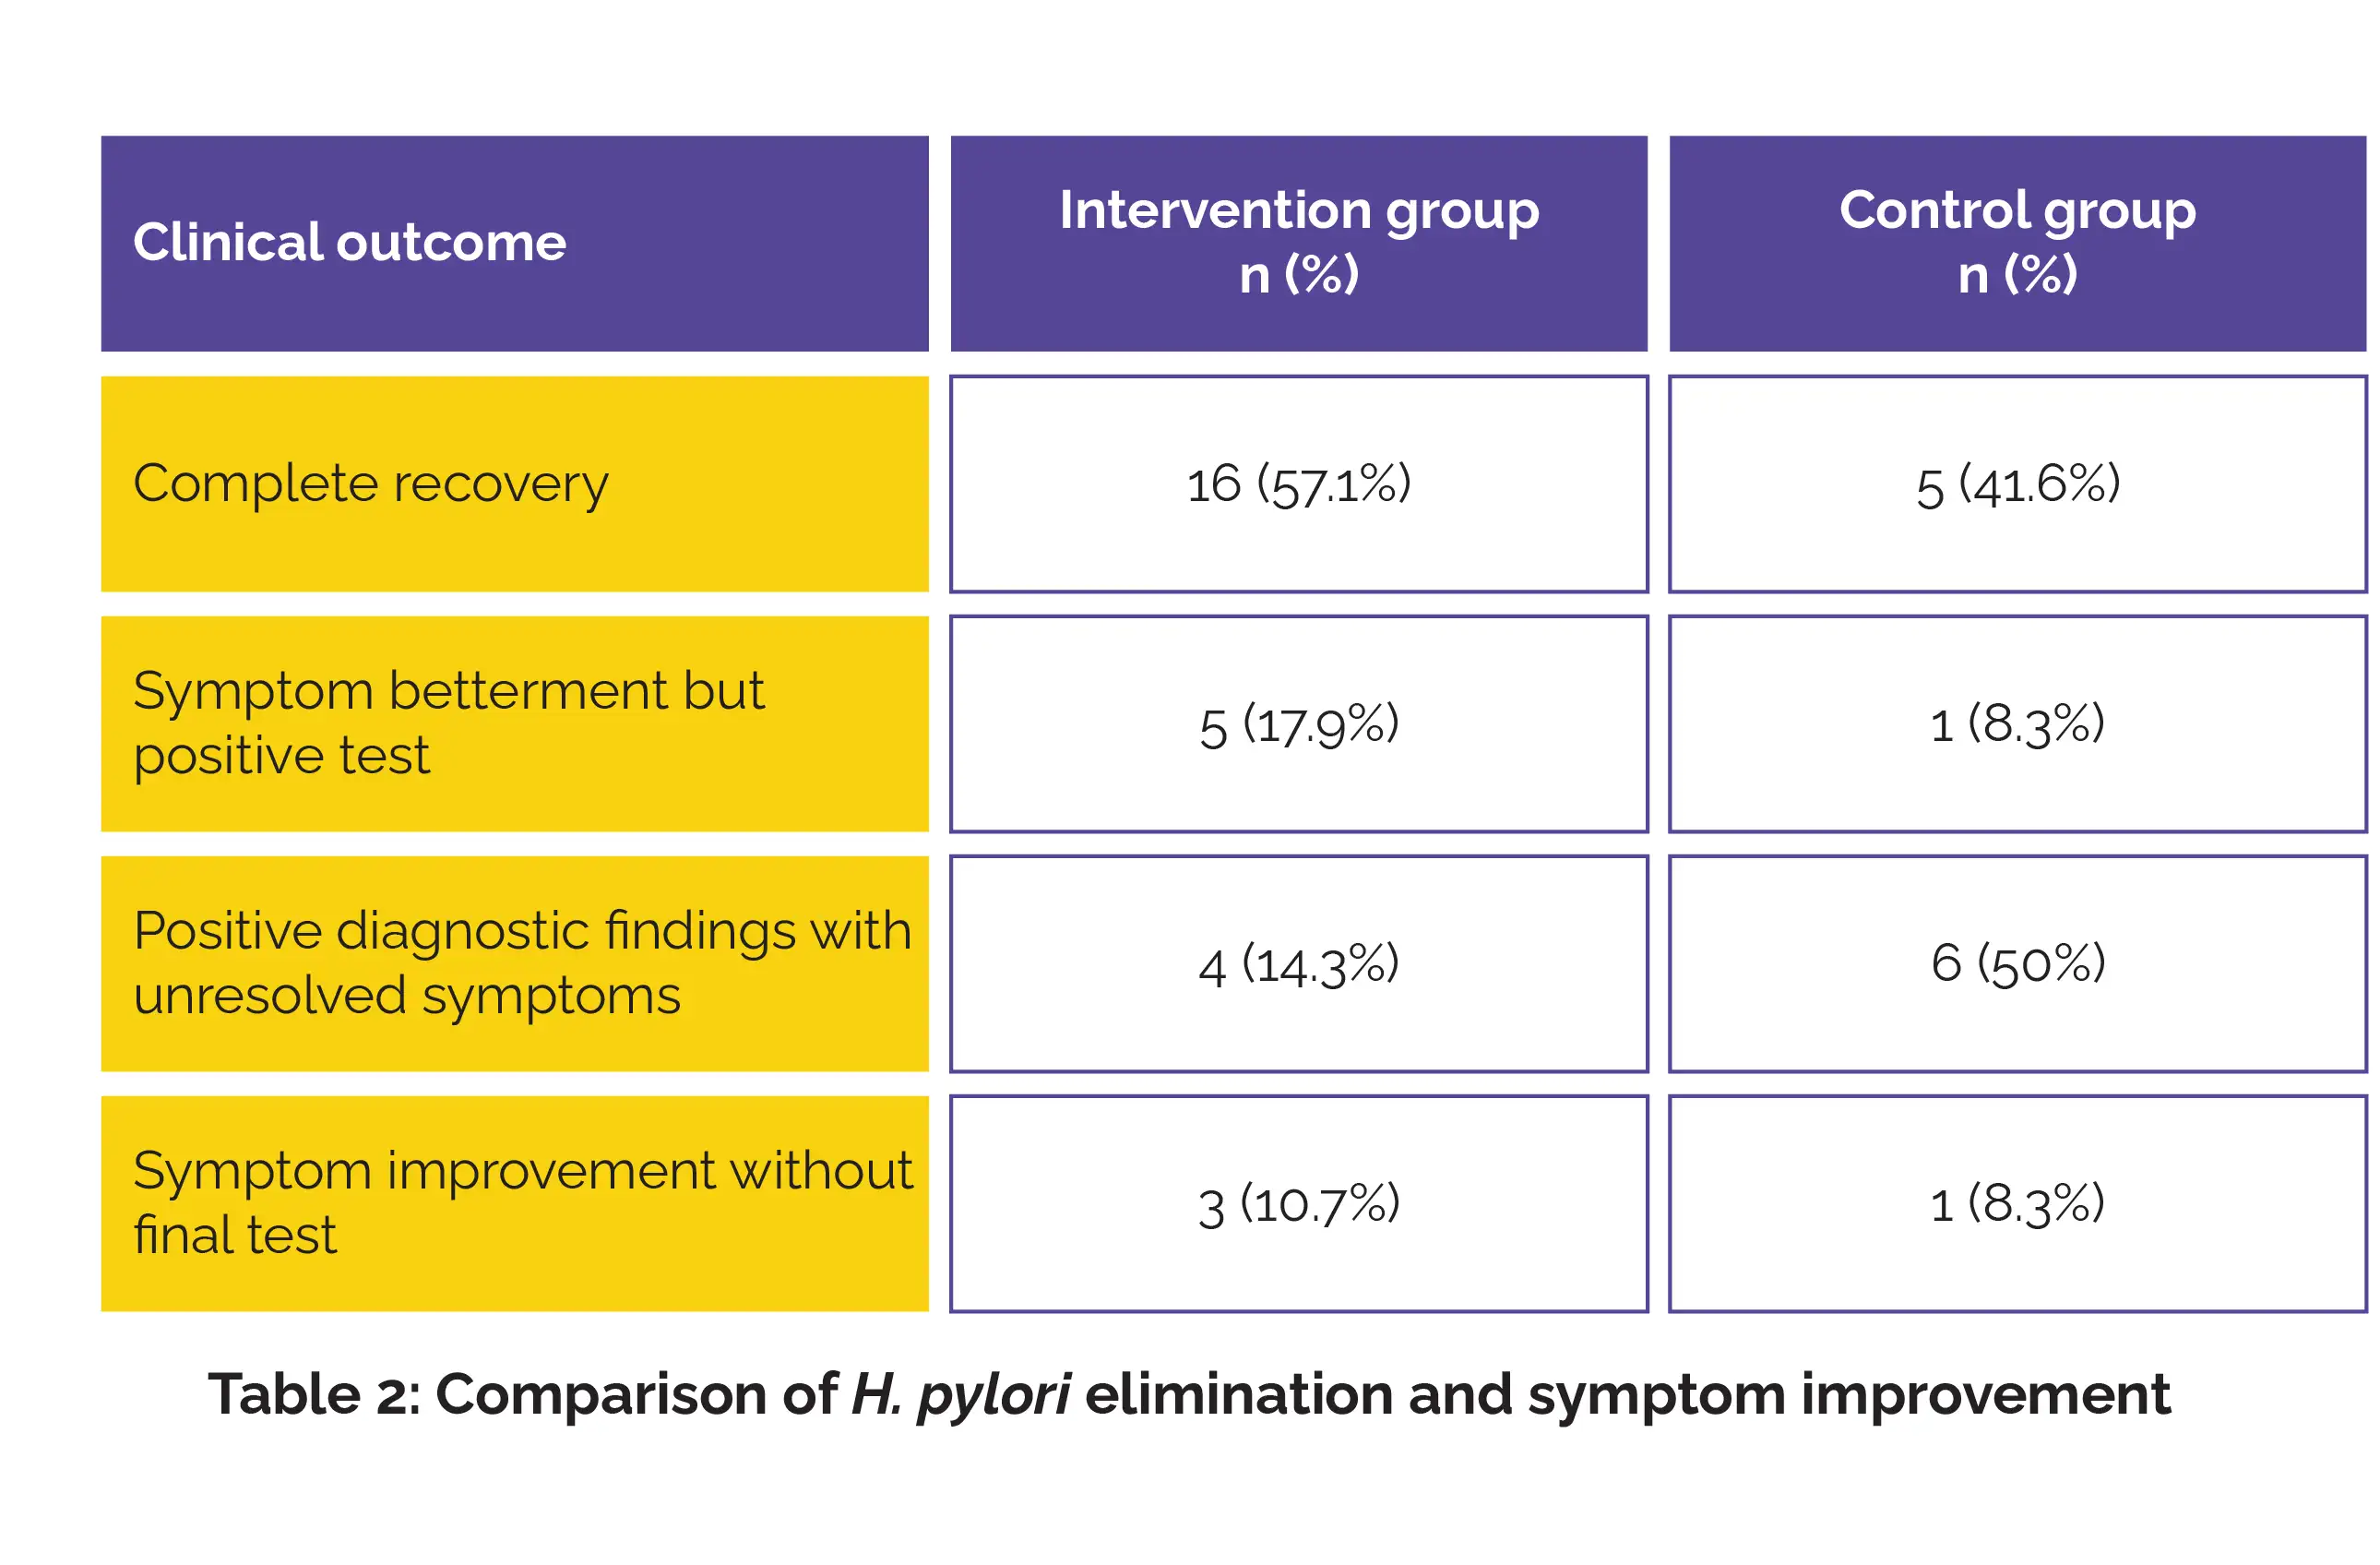
Fisher's exact test yielded p = 0.39, indicating that this difference was not statistically significant, though the authors note the small sample size restricts the power to detect a true effect (risk of type II error).
(c) AEs
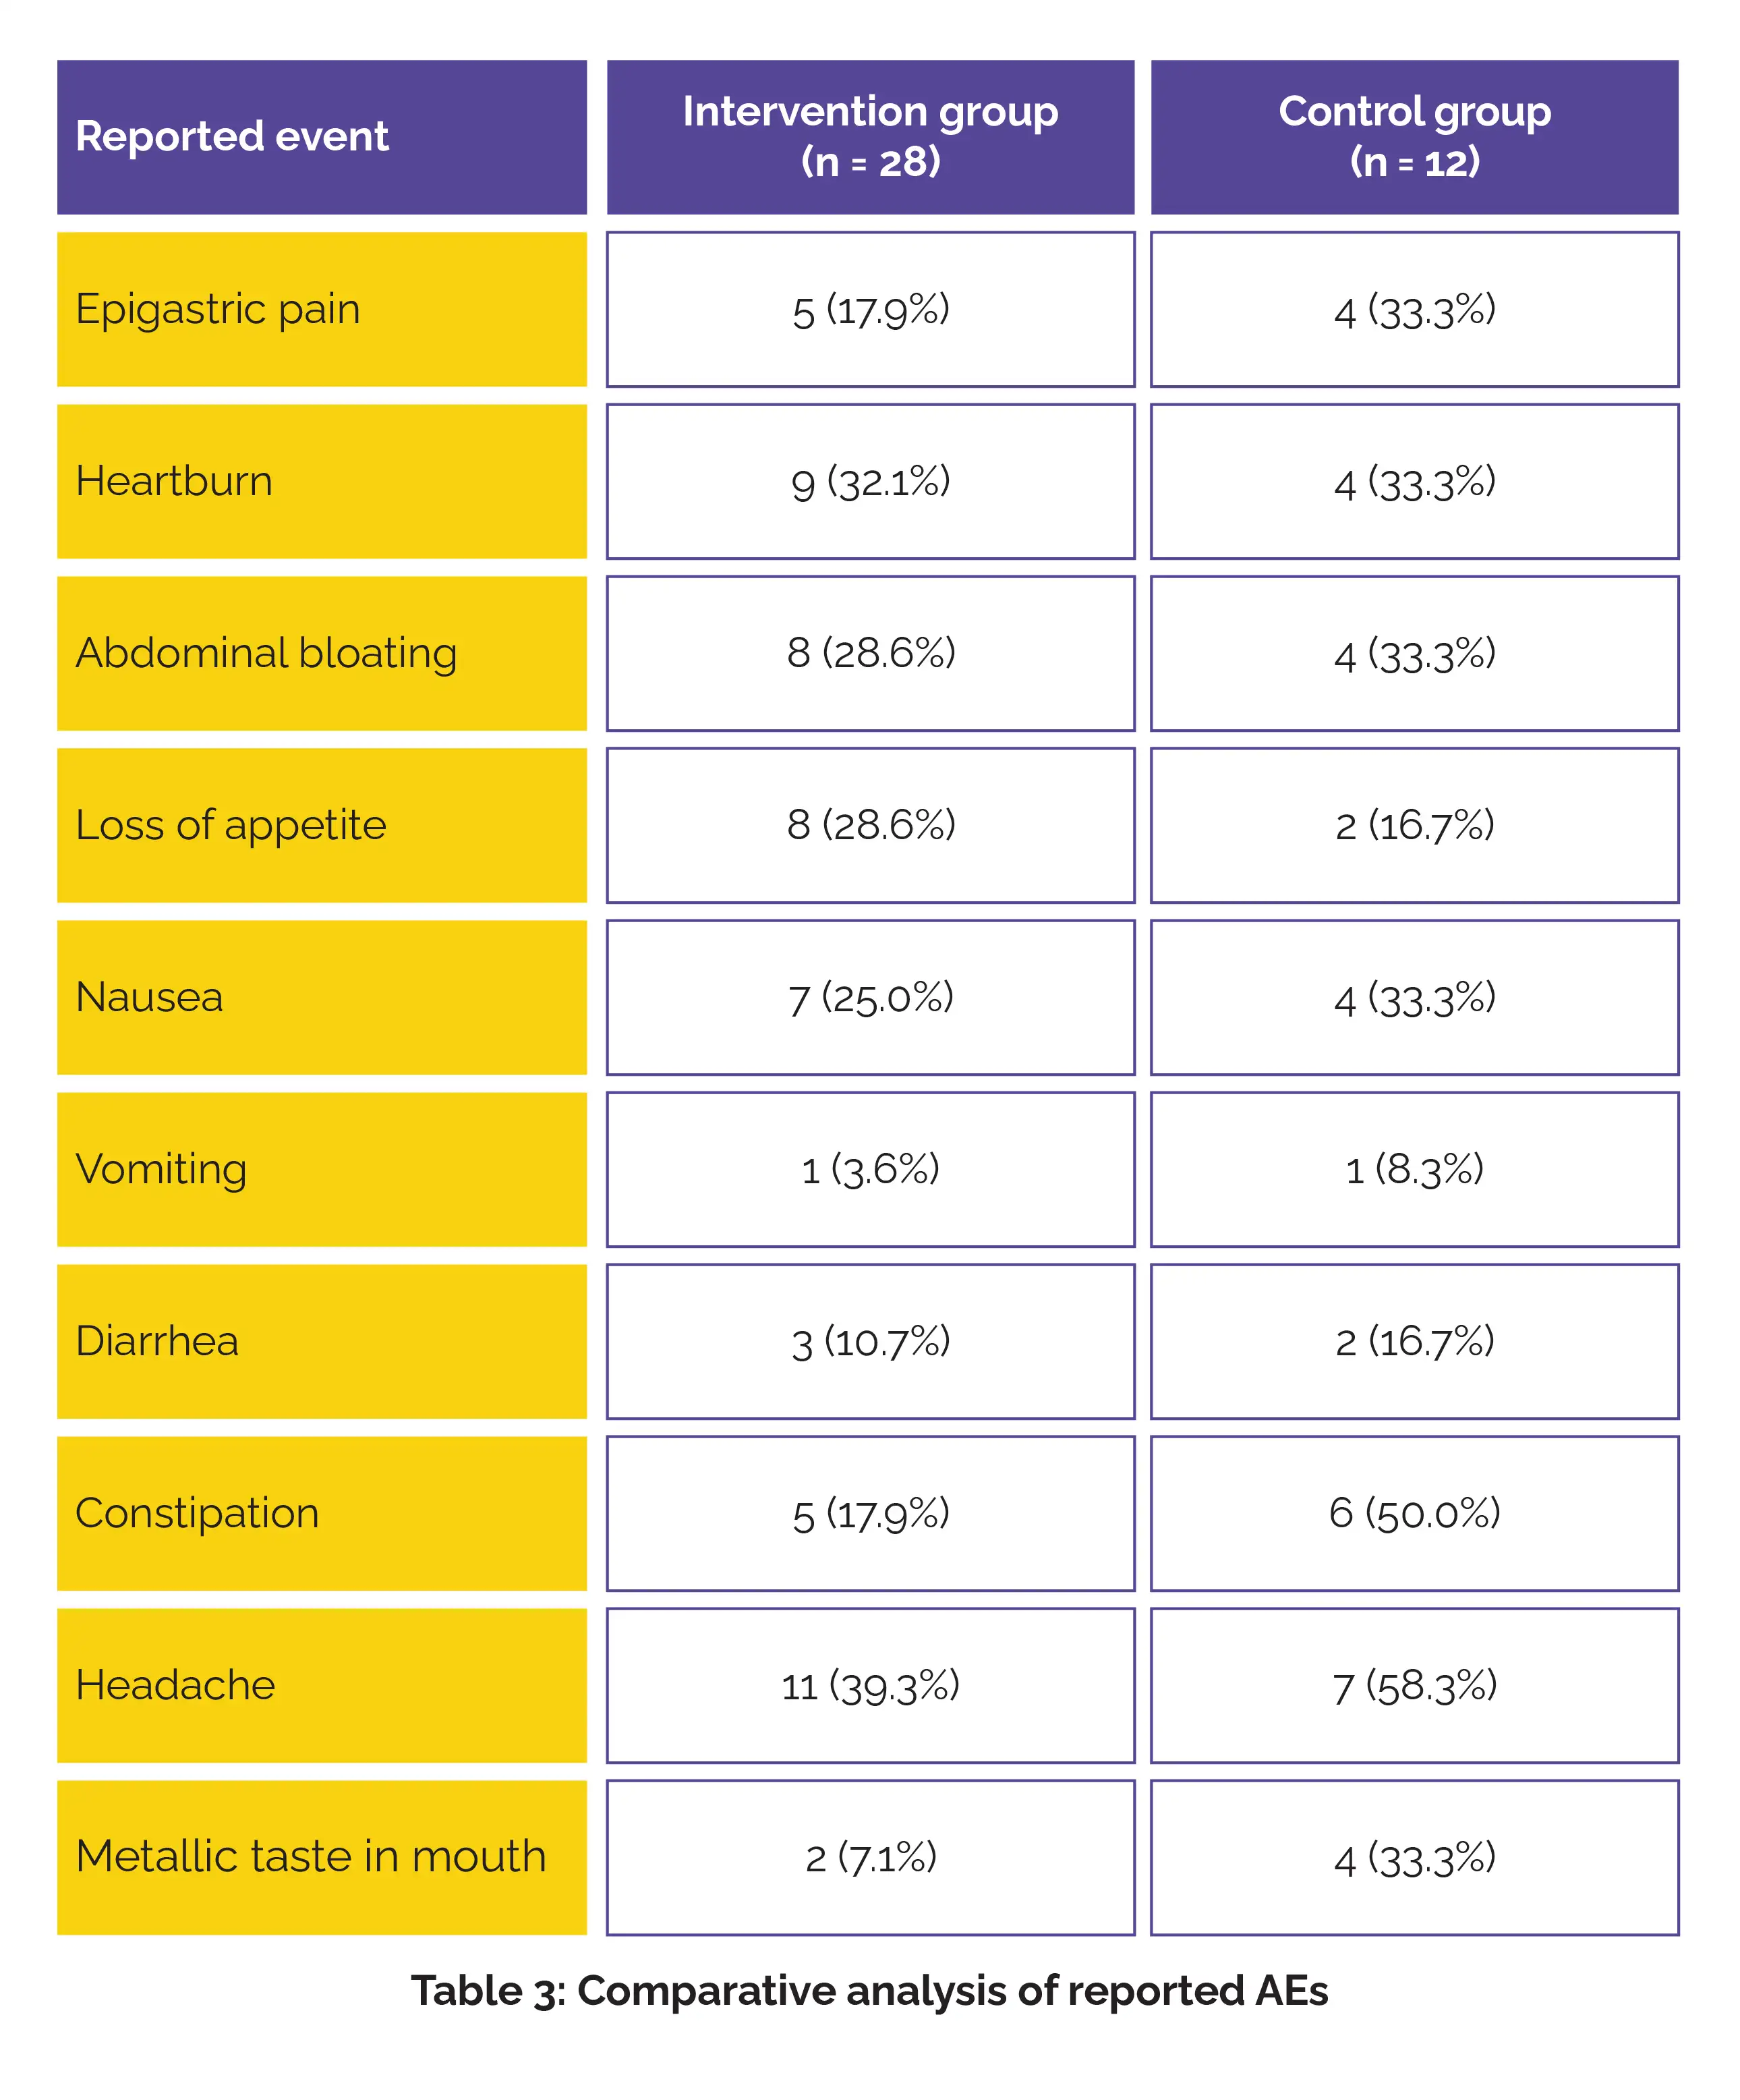
Table 3 shows that most reported symptoms and AEs were comparable between groups, with constipation and metallic taste occurring less frequently in the intervention group.
The findings demonstrated that adding a β-CD-propolis complex to standard quadruple therapy yielded clinical benefits in symptom reduction and recovery rates for H. pylori infection. Complexation with cyclodextrin successfully enhanced aqueous solubility, bioavailability, and controlled release of propolis active compounds like flavonoids and phenolic acids. Although microbiological eradication rates did not attain statistical significance, this might have been due to the limited sample size. The combined assessment of microbiological testing and symptom relief suggested a possible soothing mucosal effect and improved therapeutic utility.
Adding 250 mg/day of a β-CD–propolis complex to modified quadruple therapy resulted in complete recovery in 57.1% of evaluable patients compared with 41.6% with placebo. Prominent differences were observed for constipation and metallic taste, while physicochemical testing illustrated successful complex formation and greater propolis release than pure propolis.
BioMed Research International
Enhanced H. pylori Treatment Using a β‐Cyclodextrin–Propolis Complex: A Randomized Clinical Trial
Aisa Mehri et al.










Comments (0)